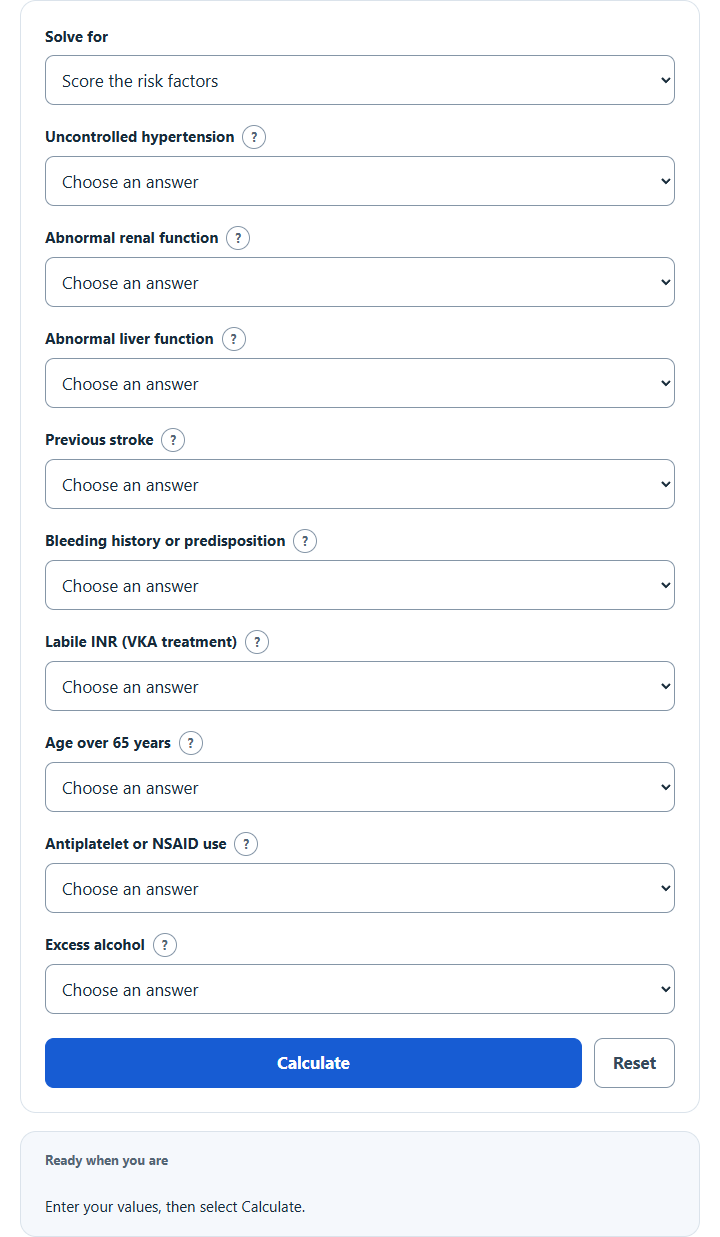
Calculate the HAS-BLED score for bleeding risk in atrial fibrillation by answering nine yes/no risk factors, then review the result with a clinician.
HAS-BLED Score Formula
The HAS-BLED score is the sum of one point for each risk factor that is present. Two of the letters cover two factors each, so they can contribute up to two points.
HAS-BLED = H + A + S + B + L + E + D
- H = Hypertension, uncontrolled with systolic blood pressure over 160 mmHg (1 point)
- A = Abnormal renal function (1 point) plus abnormal liver function (1 point), so 0 to 2 points
- S = Stroke history (1 point)
- B = Bleeding history or predisposition, such as prior major bleeding or anemia (1 point)
- L = Labile INR during vitamin K antagonist treatment: unstable/high INR or time in therapeutic range under60% (1 point). Not applicable when not receiving a VKA; unknown VKA control must not be counted as absent.
- E = Elderly, age over 65 years (1 point)
- D = Drugs that raise bleeding risk (1 point) plus alcohol use of at least8 alcohol units per week (units differ by country) (1 point), so 0 to 2 points
Each confirmed factor adds one point, from0 to9. Renal dysfunction means dialysis, transplant or creatinine≥200µmol/L (about2.26mg/dL). Liver dysfunction means chronic liver disease, or bilirubin>2×upper normal together with AST, ALT or ALP>3×upper normal. This version preserves the original age>65 boundary. Score≥3 prompts review, not automatic withholding of anticoagulation. Unknown factors prevent a completed score; known-score mode cannot identify individual factors.
Bleeding Risk by Score and Which Factors You Can Change
The first table preserves historical one-year group observations attributed to Pisters2010 and reproduced in an official protocol collection (p21). It is not a personal prediction or a universal current-treatment rate. Score5 is based on only8 patients and1 bleed; scores6–9 have insufficient data for a percentage. Group labels are descriptive review categories, not treatment rules.
| HAS-BLED score | Observed one-year percentage (%) | Risk group |
|---|---|---|
| 0 | 1.13 | Low |
| 1 | 1.02 | Moderate |
| 2 | 1.88 | Moderate |
| 3 | 3.74 | High |
| 4 | 8.70 | High |
| 5 | 12.50 | High |
The purpose is to identify risks for clinical review. The next table lists discussion topics; treatment targets and medication changes must be individualized. No score alone establishes whether anticoagulation should be started or withdrawn.
| Factor | Modifiable | Topic for clinician review |
|---|---|---|
| Hypertension | Yes | Individualized blood-pressure management |
| Bleeding predisposition | Often | Find and treat the bleeding source and correct anemia |
| Labile INR | Yes | INR control and suitability of treatment options |
| Drugs (antiplatelet, NSAID) | Yes | Review need for NSAIDs and antiplatelet medicines |
| Alcohol use | Yes | Assess alcohol intake and appropriate reduction support |
| Abnormal renal function | No | Manage the underlying kidney disease |
| Abnormal liver function | No | Manage the underlying liver disease |
| Stroke history | No | Fixed; weigh against stroke prevention benefit |
| Elderly (over 65) | No | Fixed; supports closer monitoring |
Example Problems
Example1. A72-year-old with systolic pressure>160mmHg who takes aspirin scores3 if all other factors are confirmed absent or inapplicable: age, hypertension and drugs each add1. This prompts clinician review of blood pressure and the medicine list. The historical group observation is not this person’s predicted annual risk.
Example2. A60-year-old receiving warfarin with a previous stroke and TTR50% scores2 when all other factors are confirmed absent: stroke and labile INR each add1. INR management and treatment options require clinician review; the score does not instruct a medication switch.
Frequently Asked Questions
What counts as a high HAS-BLED score? A score of 3 or more is high risk. It flags a patient who needs regular review after starting anticoagulation and whose reversible risk factors should be corrected. It does not by itself mean the patient cannot receive an anticoagulant.
Does a high score mean I should stop the anticoagulant? No. Do not start, stop, change or dose medicines from this score. Current ESC guidance says bleeding scores should not decide anticoagulant initiation or withdrawal. Discuss bleeding and stroke risks with a clinician.
How is labile INR defined? Labile INR applies to patients on warfarin whose time in therapeutic range is under 60 percent, or who have frequent high or unstable readings. It does not apply to patients on a direct oral anticoagulant, since those drugs are not monitored with the INR.