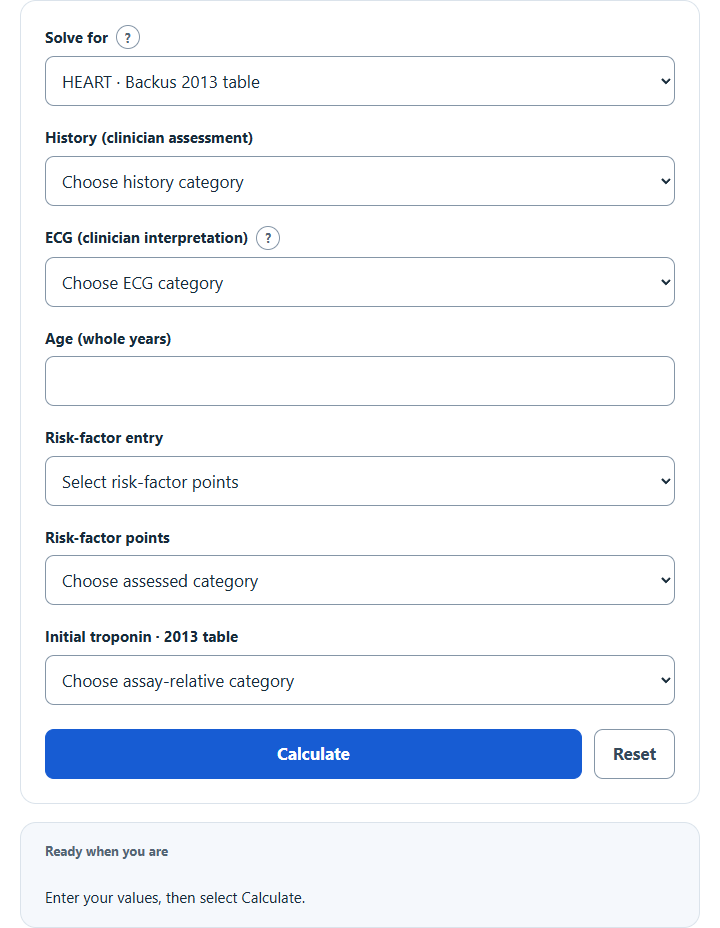
Calculate the HEART score for chest pain from History, ECG, Age, Risk factors and Troponin. It does not rule out ACS; ongoing pain needs emergency care.
Primary sources: Backus et al., 2013 prospective validation (Table 1); Mahler et al., 2015 randomized trial (Table 2 and eligibility); 2018 implementation study describing later pathway overrides. The original 2008 paper used a different troponin boundary; it is not the selected 2013 convention.
HEART Score Formula
HEART = H + E + A + R + T
Each of the five parts is scored 0, 1, or 2, so the total HEART score runs from 0 to 10. Higher groups had more major adverse cardiac events (MACE) in the cited cohorts. Group observations are not an individual probability; assay interpretation, eligibility and the complete current clinical pathway remain essential.
- H = History: 0 if the story is slightly suspicious, 1 if moderately suspicious, 2 if highly suspicious for cardiac chest pain.
- E = ECG: 0 if normal, 1 for non-specific repolarization changes, 2 for significant ST deviation not caused by a bundle branch block, LVH, or digoxin.
- A = Age: the Backus 2013 Table 1 used ≤45 = 0, >45 and <65 = 1, ≥65 = 2. The printed Mahler 2015 trial Table 2 used <45 = 0, 45–65 inclusive = 1, >65 = 2. Select the named convention; the exact endpoints differ.
- R = Risk factors: 0 for none, 1 for one or two, 2 for three or more or any known atherosclerotic disease. The counted risk factors are hypertension, high cholesterol, diabetes, obesity (BMI over 30), smoking history, and a family history of coronary disease. Qualification requires the cited protocol and clinician assessment; this calculator does not impose a universal smoking-recency or family-age definition.
- T = Troponin: Backus 2013 used ≤local upper normal limit = 0, >1 and <3 times the limit = 1, ≥3 times the limit = 2. The printed 2015 trial table used negative = 0, nonnegative up to 3 times the limit = 1, >3 times = 2. Exactly 3 times therefore differs between these tables. Use the applicable laboratory criterion, not a universal concentration.
The calculator adds the five parts under the selected table. Clinical categories start unselected. The optional helper requires an assessed yes/no status for each factor and assigns 2 points for established atherosclerosis. The historical 2015 option compares this score/troponin condition only:
2015 trial score/troponin condition = score 0–3 plus negative initial and 3-hour troponins
A met condition does not establish trial eligibility, current low-risk status or disposition. The 2015 trial enrolled ED patients age 21 or older with suspected ACS; exclusions included new ST elevation, hypotension and another illness requiring admission. Known CAD was included. Later pathways added ischemic-ECG/known-CAD overrides; this historical comparison does not silently apply those later rules or substitute for serial high-sensitivity troponin protocols.
HEART Score Risk Categories and MACE Rates
The following are six-week group observations from the Backus 2013 prospective validation cohort (n=2440), not pooled ranges or a patient-specific estimate. They must not determine disposition alone.
| HEART score | Risk category | 6-week MACE | Clinical limitation |
|---|---|---|---|
| 0-3 | Low | 1.7% | Does not establish safe discharge |
| 4-6 | Moderate | 16.6% | Assess through the complete clinical pathway |
| 7-10 | High | 50.1% | Does not prescribe a treatment strategy |
The HEART score is not the only chest pain risk tool. The table below shows how it differs from the TIMI and GRACE scores, which are built for patients who already have a diagnosis of acute coronary syndrome rather than undifferentiated chest pain.
| Score | Main inputs | Best population | What it predicts |
|---|---|---|---|
| HEART | History, ECG, age, risk factors, troponin | Undifferentiated ED chest pain | 6-week MACE, mainly to find low-risk patients |
| TIMI | Age 65+, 3+ CAD risk factors, known CAD, aspirin use, severe angina, ST change, positive marker | Suspected or confirmed UA/NSTEMI | Death, MI, or urgent revascularization at 14 days |
| GRACE | Age, heart rate, systolic BP, creatinine, Killip class, arrest, ST change, markers | Confirmed ACS | In-hospital and 6-month mortality |
These scores have different study populations, outcomes and time horizons. Selection and interpretation belong to an appropriate clinician-led chest-pain or ACS protocol; they are not interchangeable diagnoses or disposition rules.
HEART Score Example
These two cases match the calculator so you can check your inputs against the output.
Example 1. A 58-year-old has a moderately suspicious history (1), non-specific repolarization changes on the ECG (1), age 58 (1), hypertension and current smoking for two risk factors (1), and an initial troponin at the normal limit (0). The total is 1 + 1 + 1 + 1 + 0 = 4, in the 4–6 group. The 2013 cohort observed 16.6% MACE in that group; that is not this patient’s probability or an automatic disposition decision.
Example 2. A 40-year-old has a slightly suspicious history (0), a normal ECG (0), age 40 (0), no risk factors (0), and a normal troponin (0). The total is 0 under either named convention. If both initial and 3-hour troponins satisfy the historical trial negative criterion, the 2015 score/troponin condition is met. Full eligibility and current clinical low-risk status are not assessed.
HEART Score FAQ
What counts as a low HEART score? The 0–3 group is commonly called low risk. In the named 2013 cohort its six-week MACE observation was 1.7%. This is not an individual probability or a rule-out result; current protocols also assess clinical eligibility, ECG and serial assay-specific troponins.
What does the HEART score actually predict? The cited HEART studies stratified groups by six-week MACE, including myocardial infarction, coronary revascularization by PCI or CABG, or death. It is a risk stratification tool, not a diagnosis of acute coronary syndrome, so you should identify a STEMI on the ECG before you apply any score.
How is the HEART Pathway different from the HEART score? The historical 2015 trial evaluated a score plus initial and 3-hour troponins in an eligible ED population. Its printed age and troponin endpoints differ from the 2013 table, and later pathways added further overrides. This calculator names the historical table and reports only whether its score/troponin condition is met, without assigning eligibility or discharge.