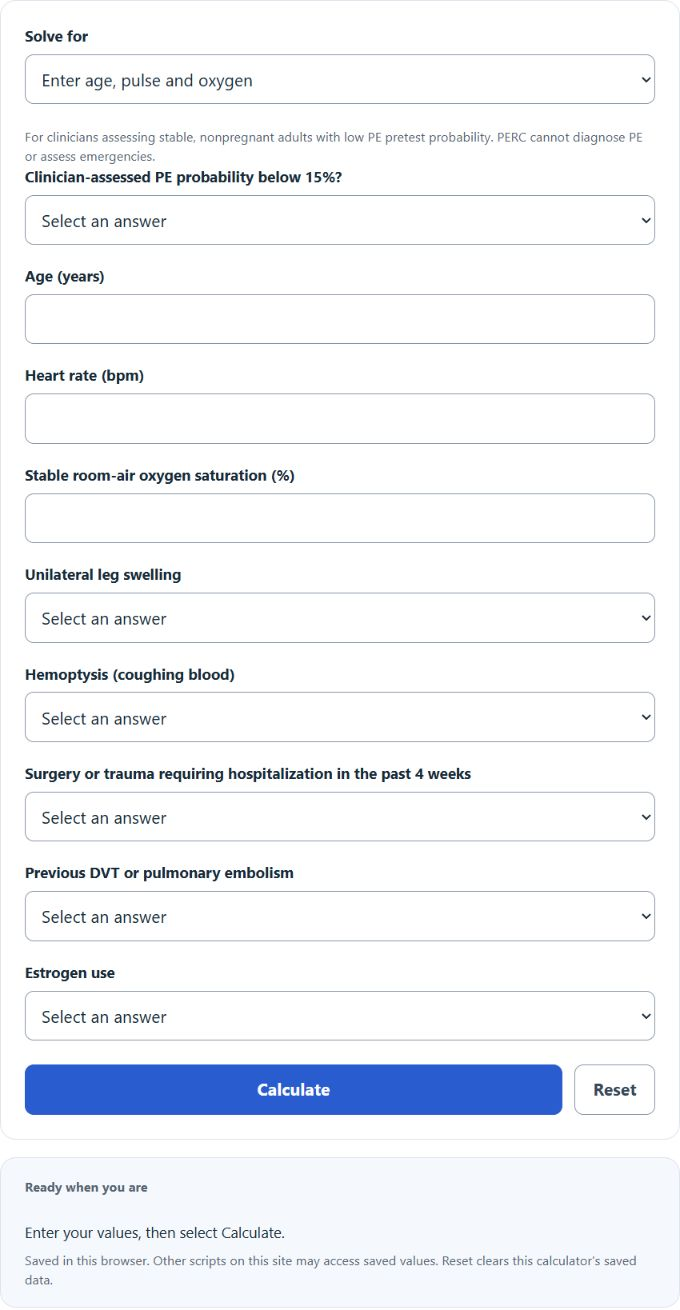
Check the PERC rule for pulmonary embolism: enter age, heart rate and oxygen saturation, answer the five other criteria, and see if all eight are negative.
PERC Rule Formula
The PERC rule is a checklist of eight criteria. Each criterion scores 1 point when it is present and 0 points when it is absent, and the points are added together:
PERC = Age + HR + SpO2 + Swelling + Hemoptysis + Surgery + VTE + Estrogen
A patient is PERC negative only when the total is 0, meaning every criterion is absent. Any score of 1 or more is PERC positive.
Variables:
- Age is 1 when the patient is 50 years or older
- HR is 1 when the heart rate is 100 bpm or higher
- SpO2 is 1 when the oxygen saturation on room air is under 95 percent
- Swelling is 1 when there is unilateral leg swelling
- Hemoptysis is 1 when the patient is coughing up blood
- Surgery is 1 when there was surgery or trauma requiring hospitalization within the past 4 weeks
- VTE is 1 when there is a prior deep vein thrombosis or pulmonary embolism
- Estrogen is 1 when the patient uses estrogen, such as oral contraceptives or hormone replacement
A positive PERC result means the rule cannot exclude PE; it does not diagnose PE or automatically require imaging. When an appropriate non-high-probability pathway uses a validated D-dimer assay, an age-adjusted reference may apply for patients older than 50:
D-dimer cutoff = Age * 10 (age over 50, ug/L FEU)
The calculator applies each threshold for you. In exact mode you enter the age, heart rate and oxygen saturation and the tool decides whether those three criteria are met; then you answer the remaining five findings Yes or No. The pretest probability selector at the top acts as a gate, because PERC is only valid once you have already judged the patient low risk. If you mark the patient as not low risk, the tool tells you the rule does not apply. A memory aid for the eight items is HAD CLOTS: Hormones, Age, DVT or PE, Coughing blood, Leg swelling, O2 low, Tachycardia, Surgery.
PERC Criteria and Age-Adjusted D-dimer Reference
The first table lists the eight criteria, the reassuring finding that scores 0, and what makes the criterion count against the patient.
| Criterion | Reassuring (0 points) | Counts against PERC (1 point) |
|---|---|---|
| Age | Under 50 years | 50 years or older |
| Heart rate | Under 100 bpm | 100 bpm or higher |
| Oxygen saturation | 95 percent or higher on room air | Under 95 percent on room air |
| Leg swelling | None or symmetric | Unilateral leg swelling |
| Hemoptysis | Absent | Coughing up blood |
| Recent surgery or trauma | None requiring hospitalization in past 4 weeks | Within 4 weeks, requiring hospitalization |
| Prior DVT or PE | No history | Prior DVT or pulmonary embolism |
| Estrogen use | None | Estrogen-containing medication |
The second table shows the age-adjusted D-dimer reference in µg/L FEU for patients older than 50 when testing is appropriate in a validated non-high-probability pathway. Confirm the assay, units and local protocol; FEU and DDU values are not interchangeable. This reference is separate from PERC and does not interpret a laboratory result.
| Age | Age-adjusted cutoff (ug/L FEU) | Standard cutoff |
|---|---|---|
| 50 or under | 500 | 500 |
| 55 | 550 | 500 |
| 60 | 600 | 500 |
| 65 | 650 | 500 |
| 70 | 700 | 500 |
| 75 | 750 | 500 |
| 80 | 800 | 500 |
Example Problems
Example 1: a PERC negative patient.
A 44-year-old with pleuritic chest pain has a heart rate of 88, an oxygen saturation of 98 percent on room air, no leg swelling, no hemoptysis, no recent surgery, no prior clot and no estrogen use. You judge the pretest probability low. Every criterion scores 0, so the PERC total is 0. The patient is PERC negative. In an appropriate stable, nonpregnant adult emergency-care population with clinician-assessed low probability, this can support no further PE testing; PE is not impossible.
Example 2: one criterion turns it positive.
A 55-year-old with the same clean history now meets the age criterion, because 55 is over 50. The PERC total is 1, so the patient is PERC positive and the rule cannot exclude PE. If D-dimer testing is appropriate in a validated non-high-probability pathway, the age-adjusted reference is 55 times 10, or 550 µg/L FEU. Confirm the assay and local protocol.
Frequently Asked Questions
What does a PERC negative result mean?
PERC negative means all eight findings are negative. In the appropriate clinical population with established low pretest probability, it can support no further PE testing. It does not mean PE is impossible, and a PERC score is not an individual numeric probability. Unknown findings must not be assumed absent.
Can you use the PERC rule on every patient?
No. A clinician must first establish low PE pretest probability, below 15% by gestalt. The 2026 multisociety guideline gives Wells below 2 as an example; Wells 4 or below is a different category and must not silently substitute. The strongest implementation trial studied adult emergency patients and excluded pregnancy, severe presentations and current anticoagulation. Do not extrapolate this calculator to children, pregnancy, unstable patients or general self-screening. Clinical judgment and local protocols remain necessary.
How is the PERC rule different from the Wells score?
The Wells score estimates how likely PE is in the first place and sorts patients into risk groups. PERC is the next step for the low risk group, asking whether that low risk patient can skip testing entirely. Wells can inform the pretest assessment; PERC cannot establish low risk itself. The clinician chooses the appropriate diagnostic pathway. Sources: 2026 AHA/ACC multisociety PE guideline, Table 3, PROPER randomized trial, and PROPER protocol.