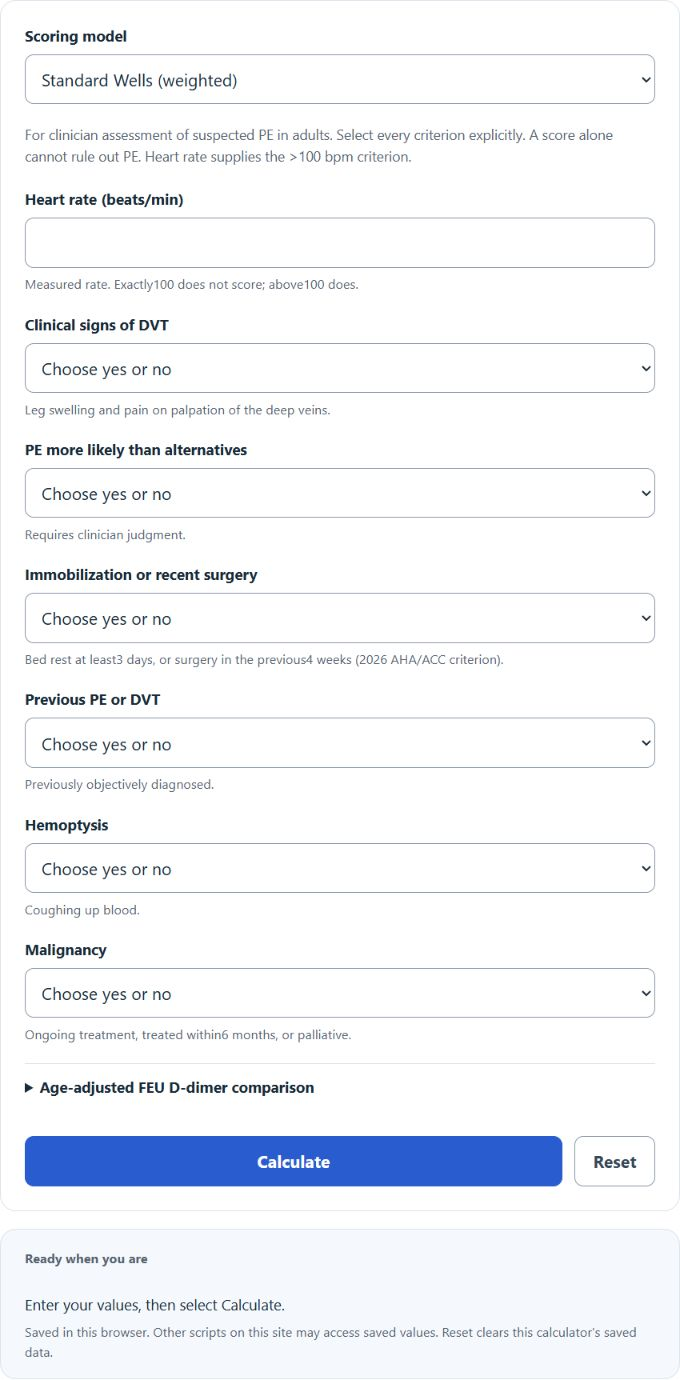
Calculate the Wells score for pulmonary embolism from seven clinical criteria, standard or simplified, with an optional age-adjusted D-dimer check.
Wells Score for Pulmonary Embolism Formula
The Wells score adds points from seven clinical criteria. The standard version uses weighted points:
Wells Score = 3(DVT signs) + 3(PE most likely) + 1.5(HR over 100) + 1.5(immobilization or surgery) + 1.5(prior PE or DVT) + 1(hemoptysis) + 1(malignancy)
A term is added only when that criterion is present, so the standard score runs from 0 to 12.5. The simplified version gives 1 point to each of the same seven criteria, so it runs from 0 to 7.
- DVT signs: clinical signs and symptoms of deep vein thrombosis, at minimum leg swelling and pain on palpation of the deep veins (3 points).
- PE most likely: pulmonary embolism is more likely than the alternative diagnoses (3 points); this requires clinician judgment.
- HR over 100: heart rate above 100 beats per minute (1.5 points).
- Immobilization or surgery: bed rest for at least 3 days, or surgery within the previous 4 weeks (1.5 points), following the 2026 AHA/ACC wording. NICE NG158 uses more than 3 days; apply the definition in the chosen clinical protocol.
- Prior PE or DVT: a previous, objectively diagnosed pulmonary embolism or deep vein thrombosis (1.5 points).
- Hemoptysis: coughing up blood (1 point).
- Malignancy: active cancer treated within the past 6 months, or receiving palliative care (1 point).
The calculator adds the six yes/no criteria and the heart-rate criterion (above 100 beats/min). Standard Wells reports three-tier and two-tier categories; simplified Wells gives one point per criterion and a two-tier category. These results support an appropriate clinical diagnostic pathway and do not independently decide testing or imaging.
Score Interpretation and PE Probability
Use the bands for the selected scoring system. The approximate prevalence figures below are historical study observations, vary by population and setting, and are not individual predicted probabilities. The calculator reports categories rather than these percentages:
| Standard score | Three-tier category | Approx. PE prevalence |
|---|---|---|
| Under 2 | Low probability | About 1 to 3% |
| 2 to 6 | Moderate probability | About 16% |
| Over 6 | High probability | About 38 to 40% |
The two-tier model draws a single line at 4 points: a score of 4 or less is PE unlikely, and a score above 4 is PE likely. In the simplified model that line sits at 1 point, so 0 to 1 is PE unlikely and 2 or more is PE likely. A "PE unlikely" result does not rule out a clot on its own. Exclusion requires a validated clinician-directed pathway and an appropriate assay; age adjustment may be used where that pathway and laboratory protocol support it. This tool does not assess pathway eligibility, pregnancy, anticoagulation, instability, or assay performance.
The table below shows the arithmetic FEU threshold: 500 ng/mL through age 50, then age times 10 ng/mL above age 50. ADJUST-PE evaluated highly sensitive assays with weighted two-level Wells (score 4 or less) or simplified revised Geneva; it did not validate this combination with simplified Wells. Use only within an eligible adult clinical pathway and local assay protocol:
| Age | Age-adjusted D-dimer cutoff (FEU) |
|---|---|
| 50 or younger | 500 ng/mL (0.5 micrograms/mL) |
| 60 | 600 ng/mL |
| 70 | 700 ng/mL |
| 80 | 800 ng/mL |
| 90 | 900 ng/mL |
In the optional section, enter both adult age in completed years and a FEU D-dimer, or leave both blank. The calculator reports whether the value is strictly below the threshold; equality is at the threshold. It does not independently exclude PE or direct imaging. For simplified Wells it reports the arithmetic comparison while explicitly qualifying that the age-adjusted combination is not established here. DDU results are outside this conversion pathway.
Example Calculations
Example 1, standard model with D-dimer. A 72-year-old has a prior DVT (1.5) and a heart rate of 108 (1.5). No other criteria apply, so the standard score is 3. That falls in the moderate three-tier band, but the two-tier result is PE unlikely because 3 is 4 or less. The age-adjusted D-dimer cutoff at age 72 is 720 ng/mL. A D-dimer of 480 ng/mL FEU is below 720. Whether PE can be excluded depends on the clinician confirming eligibility, the highly sensitive assay, and the applicable diagnostic pathway; this arithmetic comparison alone cannot decide imaging.
Example 2, simplified model, same patient. In the simplified version each criterion is worth 1 point, so the prior DVT (1) and heart rate over 100 (1) give a total of 2. A simplified score of 2 is PE likely. This differs from the weighted category; clinicians should use one established pathway consistently rather than switch scoring systems to select a preferred result. The ADJUST-PE age-adjusted strategy used weighted Wells, not simplified Wells.
Frequently Asked Questions
Does a low Wells score rule out pulmonary embolism? No. A low or "PE unlikely" score lowers the probability but does not exclude a clot by itself. An eligible patient may be assessed through a validated pathway using an appropriate highly sensitive D-dimer assay. The clinician determines further testing, imaging suitability and alternatives; this calculator cannot confirm exclusion or make those decisions.
What is the difference between the two-tier and three-tier Wells score? The three-tier model reports low, moderate, or high probability and is useful for describing overall risk. The two-tier model reports only PE unlikely or PE likely, using a cutoff of 4 points, and is designed to drive the yes-or-no decision to test or image. Both use the same seven criteria and the same point totals.
Should I use the standard or the simplified version? The standard weighted score is the original and the one most validation studies and guidelines rely on, especially when combined with age-adjusted D-dimer. The simplified version, with 1 point per criterion, is easier to score at the bedside and performs similarly in studies, but it only gives a two-tier answer. Use the scoring model and D-dimer strategy specified in an established clinical pathway; do not choose between disagreeing models after seeing their results.